


Daily Lecture 001 · 2026-11-01
Anal fissure: the diagnosis is anatomical, and so is the algorithm
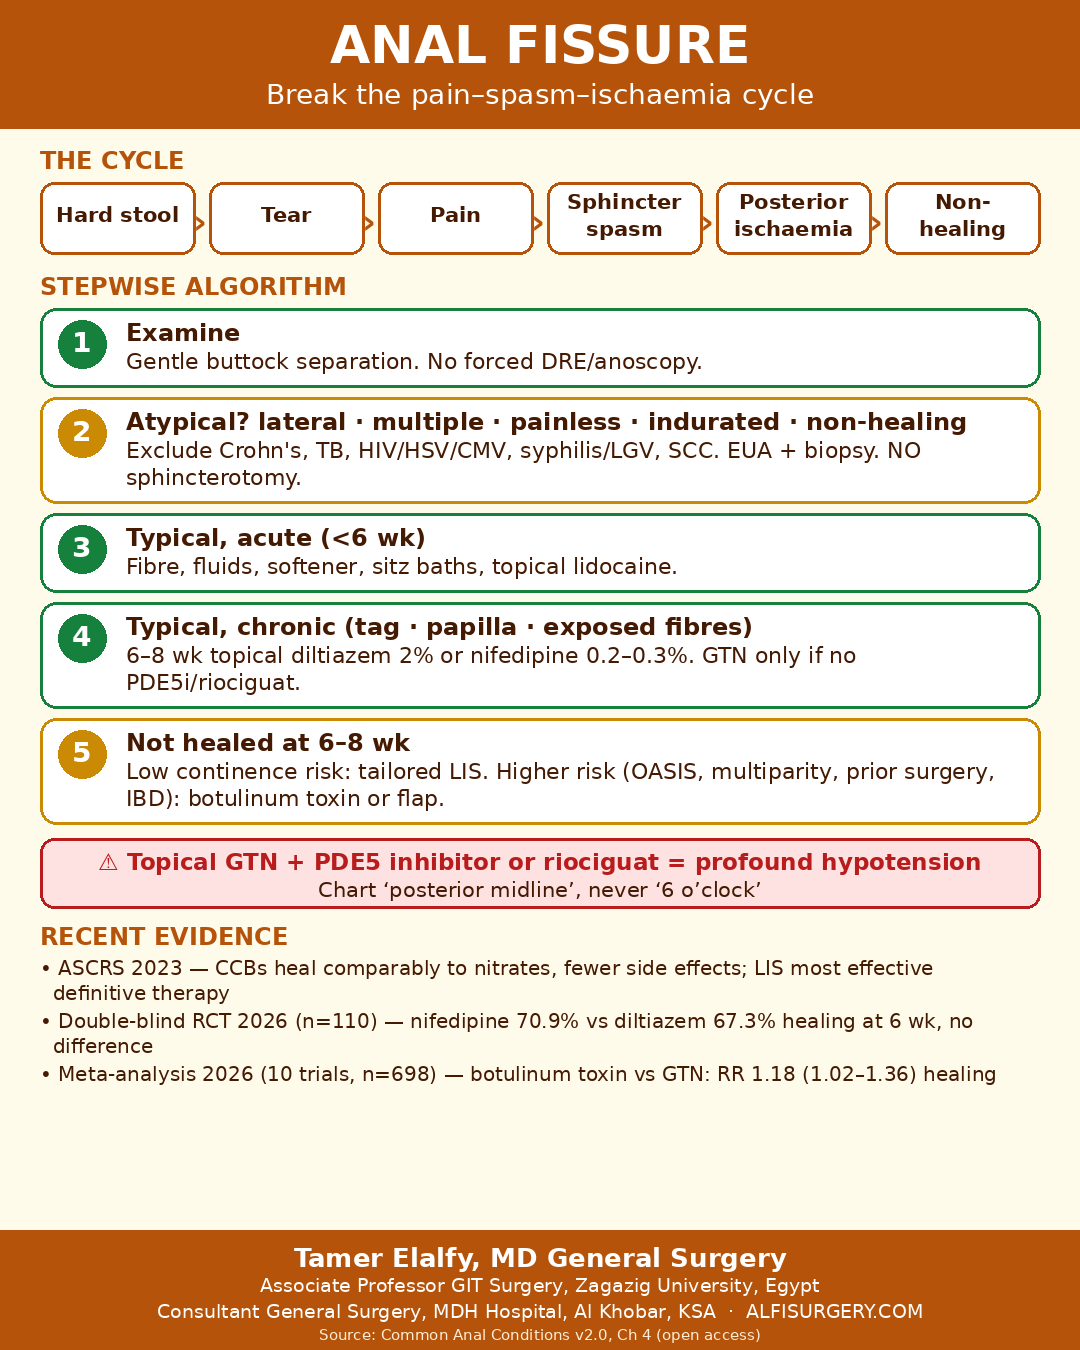
Hard stool → tear → internal sphincter hypertonia → posterior midline ischaemia → non-healing. Each treatment targets one limb of this cycle.
Stepwise approach (adapted from Common Anal Conditions, v2.0)
- Diagnose by gentle buttock separation. DRE/anoscopy is not required and is often intolerable when acute.
- Atypical (lateral, multiple, painless, indurated, non-healing)? Exclude Crohn's disease, TB, HIV/HSV/CMV, syphilis/LGV and anal SCC. EUA, biopsy, cultures/PCR. No sphincterotomy.
- Typical, acute (<6 wk): fibre, fluids, stool softener, sitz baths, topical lidocaine.
- Typical, chronic (sentinel tag, hypertrophied papilla, exposed fibres): 6–8 wk of topical diltiazem 2% or nifedipine 0.2–0.3%. GTN only if no PDE5-inhibitor/riociguat exposure.
- Failure at 6–8 wk: tailored lateral internal sphincterotomy (LIS) if continence risk is low; botulinum toxin or advancement flap if not (obstetric sphincter injury, multiparity, prior anal surgery, IBD).
Recent evidence
- ASCRS 2023: topical CCBs heal comparably to nitrates with fewer side effects; LIS is the most effective definitive therapy [1].
- Double-blind RCT, n=110 (2026): nifedipine vs diltiazem healed 70.9% vs 67.3% at 6 weeks, no significant difference [2].
- Meta-analysis, 10 trials, n=698 (2026): botulinum toxin outperformed topical GTN for healing (RR 1.18, 95% CI 1.02–1.36) with fewer headaches; recurrence was similar [3].
Topical GTN with PDE5 inhibitors or riociguat risks profound hypotension. Chart "posterior midline", never "6 o'clock".
Free open-access chapter: /books/common-anal-conditions/chapter-04
Educational content for healthcare professionals. Follow local guidelines and the treating team's judgement.
References
- Davids JS et al. ASCRS Clinical Practice Guidelines for the Management of Anal Fissures. Dis Colon Rectum 2023;66:190-199. doi:10.1097/DCR.0000000000002664
- Kumar A et al. Nifedipine vs diltiazem ointment: double-blind RCT. World J Surg 2026;50:1493-1500. doi:10.1002/wjs.70361
- Reihani H et al. Botulinum toxin vs nitroglycerin in chronic anal fissure: systematic review and meta-analysis. Biomed Res Int 2026;e6831460. doi:10.1155/bmri/6831460